
Lesson 4.B.3 - Hypothesis Test for Two Means
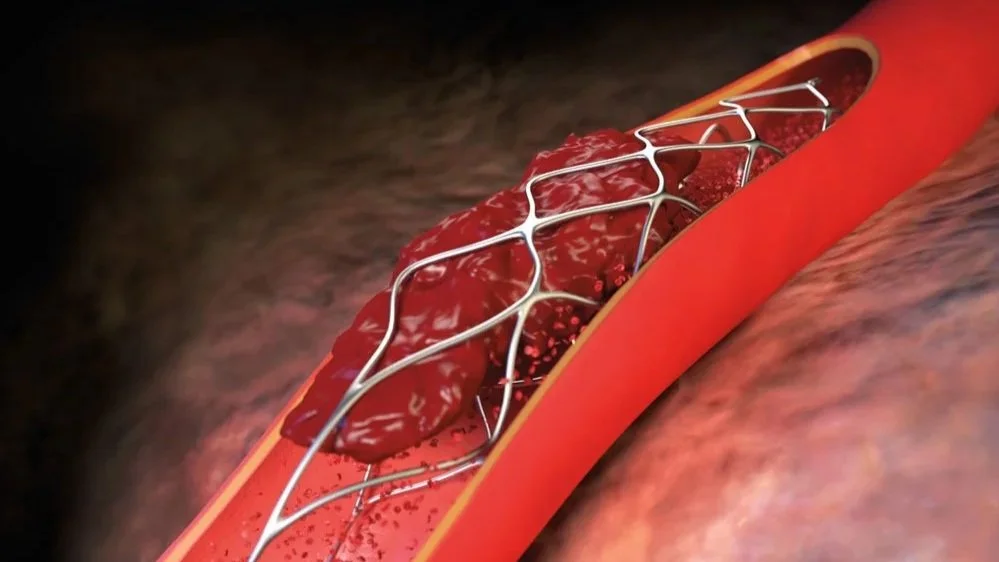
Key Question: Do stent retrievers improve stroke conditions?
Content: Two-Sample t-Test for a Difference between Two Population Means
Alignment: CED Topics 4.9-4.10
Video
Course Resources
Resources for teaching our AP® Statistics curriculum.
- Lesson Flow - timing and flow of class, using our lesson materials
- Pacing Guide - pacing our units, with daily or block schedules
- CED Alignment Guide - aligning our lessons to the AP® Statistics Course and Exam Description
Teaching Resources
Resources for teaching with Skew The Script.
- Discussion Norms - our model discussion norms for the classroom
- Letter to Parents - letter to share with parents about our nonpartisan approach
- Teaching Math on Civic Topics - tips for teaching math lessons that cover civic topics
Lesson Notes
Lesson-specific insights from the creators of this lesson.

Traditionally, less than 40% of people who experienced strokes due to large vessel clots regained functional independence (ability to live by oneself, cook, manage finances, etc.). In 2015, to improve patient outcomes, researchers tested a new device: the stent retriever. The device is a metal mesh attached to a wire, which can be inserted into brain blood vessels to trap and remove clots. Dr. Jeffrey Saver (the father of Skew The Script’s founder Dashiell Young-Saver) was a principal researcher for the study. In this lesson, we walk through Dr. Saver’s research, to see if the new device significantly improved patient outcomes.
- Check conditions for a two-sample t-test for a difference between population means
- Conduct a two-sample t-test for a difference between population means
Before proceeding: Familiarize yourself with the lesson materials linked above (e.g. handout, handout key, slides, video). Then, for additional background and teaching tips from the lesson creators, check out the sections below.
- The beginning of the lesson discusses how strokes occur and their impacts on patients. Some students may have family members or other loved ones who have experienced strokes. For these students, discussing treatments and breakthroughs for the disease can be motivating and empowering. However, it could also resurface trauma or loss. We recommend giving students an anonymous survey (on paper or digitally) before this lesson, asking students whether discussion of data related to stroke (from a clinical perspective) would resurface trauma. Instructors can explain that the lesson will cover data related to a new treatment for stroke and that discussion will center on the effectiveness of that treatment, rather than individuals’ experiences with the disease. If any student responds “yes” to the anonymous survey, we recommend using one of the practice problems (which cover different contexts) as the main teaching example, rather than the stroke research example.
- Before introducing the test statistic, we recommend asking students whether the observed 0.97 point difference seems convincing. Could this difference have occurred by chance? What do they think?
- This lesson brings together the hypothesis-testing logic from Lesson 4.A.4 and the two-sample setup from Lessons 4.B.1 and 4.B.2. Ask students to identify what carries over from those lessons. The first Practice problem then provides students with the opportunity to sort among the inference procedures learned so far, before doing any calculations.
First, download this lesson's Handout Key and read through its Discussion Question section. Then, check out our model discussion norms and the additional background notes below.
- If students want to stop the cholesterol trial because the treatment group’s mean is below 200 mg/dL, ask: “Does a lower sample mean establish that the drug works? Or could the results have happened by chance? How can we tell?” The one-sided test gives a p-value of about 0.057. At the usual 5% significance level, we do not yet have convincing evidence that the drug truly lowers mean cholesterol. This provides a reason to continue gathering evidence.
- The discussion connects statistical errors to real consequences. Ask students what could happen if an ineffective drug were declared effective, and what could happen if researchers delayed recognizing a helpful drug. Also ask what information about side effects they would want before making a decision. A p-value alone cannot resolve all of these concerns.
- There is an important distinction between a planned interim analysis and repeatedly checking the data until a p-value falls below 0.05. Repeated testing with the same cutoff increases the chance of a Type I error. This is called the “problem of multiple tests” – a concept which is outside the scope of the AP Exam, but that we briefly discuss in Lesson 3.A.8 as an extension topic. So, instead of repeatedly checking for statistical significance at arbitrary intervals, trials can use pre-planned stopping rules that account for these multiple tests. Continuing the cholesterol trial should mean following that plan, rather than choosing the next check because the current result is “almost significant.” These methods extend beyond this lesson; the FDA’s guidance on adaptive trials provides additional background.
- The full paper by Dr. Saver and colleagues, published in the New England Journal of Medicine in 2015, reports the SWIFT PRIME trial. Both groups received the clot-dissolving drug t-PA; one also received the stent-retriever procedure. The comparison therefore concerns the added benefit of the procedure. The patients had strokes caused by large-vessel blockages, so the findings should not be extended to every type of stroke.
- The paper reports 196 randomized patients, but disability-outcome data were only available for 98 patients in the stent group and 93 in the control group. The lesson uses these 191 patients.
- The disability score is an ordinal scale: its categories have an order, but a one-point change could represent different amounts of functional change in patient health. For example, reducing a patient’s disability outcome from 2 → 1 on this scale may look very different from reducing their disability outcome from 5 → 4. In other words, one reduction might be more substantial (in terms of patient health and life outcomes) than the other. For simplicity, this lesson treats the disability scores numerically, to practice comparing means. The published study used a more complex method (outside the scope of this course), which detects shifts in the whole distribution of disability scale scores (rather than just shifts in the mean).
- For two-sample t procedures, most software and calculator platforms use the Welch–Satterthwaite equation to determine the degrees of freedom. The equation and its derivation are far beyond the scope of our course. But students may benefit from knowing that the degrees of freedom from this equation usually are higher than the more conservative estimate we use when determining the degrees of freedom for two-sample procedures by hand (n – 1, where n is the sample size from the smaller group). So, the underlying t-distribution used by software and calculator platforms will tend to be more precise than the manually-calculated t-distribution, yielding slightly lower p-values. The degrees of freedom and associated p-values from both methods (from software or by hand) will both be accepted on the AP Exam.
- Random assignment allows a cause-and-effect conclusion about adding the stent procedure for patients like those studied. It does not establish that these patients represent everyone who has a stroke. Contrast this with the library-attendance example in Practice Problem 4: independently sampled days can support a comparison of mean attendance, but they cannot establish that the renovations caused the difference between schools.
Student Supports
Lesson-specific resources to support all learners.
- As students learn two-sample procedures, they will need to distinguish them from the matched pairs procedures introduced in Lessons 4.A.3 and 4.A.5. Reinforce that two groups do not necessarily mean two independent samples: if observations across the groups have a meaningful pairing, such as two measurements from the same person or from identical twins, a matched pairs procedure is appropriate; otherwise, the groups should be treated as independent samples and a two-sample procedure is appropriate.
- To help students keep track of the direction of the difference, encourage students to write “stent minus control” before setting up their hypotheses. Because lower disability scores represent better outcomes, negative differences correspond to an improvement from the procedure. You can also ask students to shade the appropriate tail (left-tail) before using technology.
- Continuing to use the “in a world where” framing can help students interpret the p-value: “In a world where the stent makes no difference, there is about a 0.0001 probability of observing a -0.97 point difference in mean disability score (or less) by chance alone.”
- Difference between population means
- Standard error
- Degrees of freedom
- Statistical significance
- Type I error
- In addition, the following contextual terms may need clarification or a definition provided:
- Stroke
- Blood clot
- Stent retriever
- Disability score
- Functional independence
- Standard of care / control group
- Clinical trial
- Monitoring committee
- The word “significant” has a narrower meaning in statistics than in everyday speech. A statistically significant difference provides evidence against the null hypothesis at the chosen significance level. It does not, by itself, tell us whether an effect is large or practically important.